2026 How to Stop a Patient Sliding Down an Electric Bed

Time:2026-10-28 Author:Ethan
0%

Electric beds improve positioning, transfers, and comfort, but they can also create a gradual sliding problem. A patient may start upright, then slowly move toward the footboard as the backrest rises. Shear, friction, weak core control, slippery bedding, pain, and poor foot support can all contribute. Why is my patient sliding down in their electric bed? The answer usually involves several interacting factors, not one faulty adjustment.

The Agency for Healthcare Research and Quality reports that hundreds of thousands of hospitalized patients fall each year, with many falls causing injury. Sliding is not always a fall, but it can increase unsafe repositioning, skin stress, and caregiver lifting demands. The National Pressure Injury Advisory Panel identifies shear and friction as important contributors to tissue damage. A warm room, damp clothing, or wrinkled sheets may make the problem worse. Small details matter.

Start with observation. Check the patient’s posture, alertness, pain, footwear, and ability to follow instructions. Assess whether the bed height, knee section, backrest, and mattress support match the care plan. The Joint Commission emphasizes individualized fall-risk assessment and reliable prevention practices, rather than relying on one device. Bed rails also require caution because they may create entrapment or climbing risks. They are not a substitute for assessment.

This guide examines practical, evidence-informed ways to reduce sliding in electric beds. It also recognizes an uncomfortable truth: a familiar routine may still be unsuitable for one patient. Recheck positioning after movement, meals, sleep, and personal care. Document what changed. Seek advice from nursing, rehabilitation, or tissue-viability professionals when sliding persists, skin reddens, or the patient reports pain.
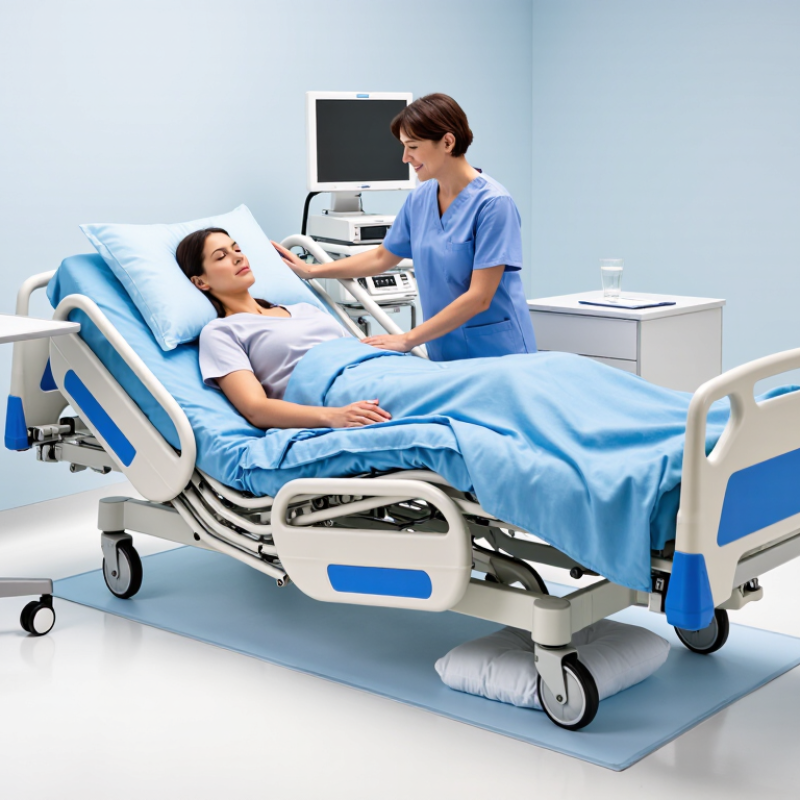
2026 How to Stop a Patient Sliding Down an Electric Bed

Why Patients Slide Down Electric Beds

Why do patients slide down electric beds? The cause is usually a chain, not one faulty setting. Raising the head section bends the mattress. Gravity then pulls the pelvis toward the footboard. If the knees remain flat, the body has little counterforce. Weak abdominal muscles, reduced sensation, sedation, pain, and dizziness make self-correction harder. Moist skin or loose bedding can further reduce friction. The bed is often blamed too quickly.

At the bedside, clinicians may see pelvic tilt, a rounded posture, or heels pressing into the mattress. These details matter because sliding creates shear at the sacrum, not only movement.

AHRQ’s PSNet review reports approximately 700,000 to 1 million inpatient falls annually in the United States. It also cites rates of 3–5 falls per 1,000 bed-days. The report does not say every fall begins with sliding. It does show why small positioning changes deserve serious attention. WHO reports about 684,000 fatal falls globally each year, with adults over 60 carrying the highest burden.

Electric movement can amplify the problem when the knee section is not raised with the back section. A narrow mattress, poorly fitted sheet, or elevated foot position may add pressure. Patient size and body shape matter, too. There is no universal angle. A safer assessment checks pelvic alignment, comfort, alertness, skin moisture, and repositioning ability. Staff should follow the bed’s instructions and local clinical policy, then reassess after each adjustment. This is less dramatic than blaming equipment, but more accurate. Small omissions remain common.

How to Assess the Patient and Bed Position

2026 How to Stop a Patient Sliding Down an Electric Bed

How to Assess the Patient and Bed Position

Before changing the bed, assess the patient, not only the visible sliding. Ask about pain, dizziness, weakness, numbness, and breathing comfort. Observe hip alignment, foot position, skin moisture, and the patient’s ability to follow instructions. Check for confusion or sudden changes in strength. These findings may require clinical review before repositioning.

Then inspect the bed position carefully. Confirm that the brakes are engaged and the bed is stable. Check whether the head section is too steep for the patient’s condition. A sharply raised backrest can push the trunk forward. The knee section may need adjustment to support the thighs and reduce downward movement. Keep the patient’s feet supported when appropriate. Avoid creating pressure behind the knees.

Explain each movement before starting. Use the facility’s approved repositioning method and ask for assistance when the patient cannot cooperate. Do not pull the patient by the arms or shoulders. Lines, drains, oxygen tubing, and fragile skin need continuous attention. Reassess after every adjustment. Is the patient centered? Are the heels protected? Can the patient breathe and communicate comfortably?

A practical check can still miss something. I have seen staff focus on bed angles while overlooking a wet gown or poorly placed pillow. Patient size, mattress condition, and muscle control also change the result. Document the assessment and response, then follow local clinical guidance when sliding continues.

How to Adjust the Electric Bed Safely

2026 How to Stop a Patient Sliding Down an Electric Bed

Sliding often begins when the head section rises too sharply. The patient’s hips move forward, creating pressure and discomfort. Before adjusting the bed, explain each movement and check the patient’s pain, balance, and ability to follow instructions. Lock the bed wheels, keep the floor clear, and raise the bed to a safe working height. Adjust the backrest gradually, then support the knees if the bed allows. A slightly raised knee section can reduce forward movement, but settings must match the patient’s condition and the bed’s instructions. Never force a posture. Stop if the patient reports pain, dizziness, numbness, or breathing difficulty. Small changes matter.
Tips: Keep the hips near the bed’s pivot point. Use pillows only when approved by a clinician. Check that heels are supported and clothing is not bunching beneath the body. Reassess after every adjustment. A caregiver should not pull a patient upward alone; use trained assistance and suitable repositioning equipment when needed.
Observe the patient for redness, skin shear, or repeated sliding. These signs may indicate poor positioning, weakness, medication effects, or an unsuitable mattress angle. Record what adjustment helped and share it with the healthcare team. I have found that rushing this step causes more sliding later. The safest setting is not always the lowest one. It is the one the patient can tolerate, breathe comfortably in, and maintain without strain.

How to Reposition and Support the Patient

How to Stop a Patient Sliding Down an Electric Bed

Repositioning should begin with assessment, not bed controls. Check pain, alertness, skin condition, tubing, and movement ability. The 2019 international pressure injury guideline recommends individualized repositioning based on tissue tolerance, mobility, skin status, and support surfaces. AHRQ reports that pressure injuries affect about 2.5 million hospitalized patients annually in the United States. Sliding increases shear, especially around the sacrum.

Lock the wheels and explain each step. Use a friction-reducing sheet, ideally with two trained caregivers. Flatten the head section when appropriate, support the knees, and move the patient upward without pulling the arms or shoulders. Raise the head slowly afterward, keeping the pelvis centered. Place pillows beside the trunk, under the calves, or between the knees. Keep the heels floating when clinically suitable. Check breathing, comfort, catheter lines, and skin folds. Small details matter.

Tips: Reassess after every adjustment. Watch for redness that does not fade, new pain, or numbness. Do not rely on the electric bed alone. A bed can reposition a patient, but it cannot judge tissue tolerance. Incomplete practice happens; rushing is a warning sign. If the patient still slides, review hip angle, knee support, mattress pressure, and the care plan with a registered nurse or rehabilitation professional.

How to Prevent Future Sliding and Monitor Comfort

Sliding in an electric bed often starts when the head section rises without enough knee support. The pelvis moves forward, creating shear at the sacrum and pressure behind the knees. AHRQ’s 2023 Patient Safety Primer estimates 700,000 to 1,000,000 hospital patients fall each year. Prevention needs more than a quick pull upward.

Before raising the backrest, check the care plan and explain the movement. Place the hips deep against the bed’s bend. Raise the knee section when clinically appropriate, then adjust the head slowly.

Keep the bed low, wheels locked, and the call bell within reach. Avoid pulling the patient by the arms. Use an approved repositioning aid and enough staff. NPIAP guidance supports individualized repositioning and regular skin checks, especially for patients with limited mobility or reduced sensation.

Tips: Recheck comfort after five minutes. Ask about pain, numbness, sweating, breathing, and pressure. Look for wrinkled sheets, red skin, or a gap beneath the knees. Document the position, support used, and patient response. A small change in pelvic alignment can prevent repeated sliding. Still, a checklist is not enough. Sedation, weakness, and fear may be missed. Reassess after meals, therapy, sleep, and every bed adjustment. Follow facility policy and the patient’s clinical plan. (AHRQ, 2023; NPIAP, 2019)

FAQS

Why does a patient slide down in an electric bed?

Sliding often begins when the head section rises without enough knee support. The pelvis moves forward. Shear may develop near the sacrum.

What should caregivers assess before repositioning?

Check pain, alertness, skin condition, tubing, and movement ability. Also ask about numbness or fear. Do not start with bed controls alone.

How can caregivers move a patient upward safely?

Lock the wheels and explain each step. Use an approved friction-reducing sheet with enough trained caregivers. Never pull the arms or shoulders.

How should the bed be adjusted during repositioning?

Flatten the head section when appropriate and support the knees. Move the patient upward with the pelvis centered. Raise the head slowly afterward.

Which supports can improve comfort and positioning?

Place pillows beside the trunk, under the calves, or between the knees. Keep the heels floating when clinically suitable. Check for gaps beneath the knees.

How can future sliding be reduced?

Place the hips deep against the bed’s bend. Raise the knee section when appropriate, then adjust the head slowly. Keep the bed low and the call bell nearby.

What signs show that repositioning needs review?

Watch for lasting redness, new pain, numbness, sweating, or breathing changes. Wrinkled sheets may increase pressure. Small alignment errors matter.

How often should comfort and skin condition be reassessed?

Recheck comfort after five minutes and after every bed adjustment. Reassess after meals, therapy, and sleep. Honestly, rushed checks can miss weakness or fear.

What should caregivers do if the patient keeps sliding?

Review hip angle, knee support, mattress pressure, and pelvic alignment. Check the care plan with a registered nurse or rehabilitation professional. The bed cannot judge tissue tolerance.

Conclusion

Patients may slide down an electric bed because the backrest is raised too sharply, the bed is positioned too flat, or the patient lacks sufficient trunk, hip, or leg support. “Why is my patient sliding down in their electric bed?” is an important assessment question. Check the patient’s posture, comfort, physical ability, skin condition, and risk of injury, while also confirming that the mattress and bed position are appropriate. Keep the patient’s head, shoulders, hips, and legs aligned, and avoid creating excessive pressure or bending at the joints.

Adjust the electric bed gradually and explain each movement to the patient. Lower the backrest slightly when appropriate, raise the knees or leg section to reduce forward sliding, and use approved positioning supports according to the patient’s care plan. Reposition the patient gently with assistance when needed, maintaining dignity and checking for pain, breathing difficulty, or skin irritation. Regularly monitor comfort, alignment, and movement, and reassess the setup after meals, transfers, or changes in condition. Consistent observation and individualized support can help reduce sliding and promote safer rest.

Ethan

Ethan

Ethan is a seasoned marketing professional with a deep expertise in our company's innovative product line. With a passion for sharing knowledge and insights, he takes the lead in regularly updating our corporate blog, where he explores industry trends, product features, and effective marketing......